
Simple, evidence-based ways to boost milk supply: nursing and pumping schedules, power pumping, latch help, paced bottle feeding, hydration, galactagogues, a...
Is My Baby Getting Enough Breast Milk?

Sarah Mitchell
Sarah Mitchell is a Registered Pediatric Nurse and a mother of three who has spent over a decade helping families navigate the beautiful, chaotic early years of childhood. She combines evidence-based medical knowledge with real-world parenting experience to offer practical, compassionate advice. At Awesome Parent, Sarah's mission is to help exhausted parents find solutions, trust their instincts, and finally get some sleep.
At about 3 a.m., every breastfed parent eventually has the same thought: “Is this baby actually getting anything?” I’ve had that thought as a pediatric triage nurse, and I’ve absolutely had it as a mom, staring at a tiny newborn who seemed determined to nurse forever.
The tricky part is that breastfeeding is a hidden process. You can’t see ounces going in. The good news is we have several reliable, boring (in the best way) ways to check whether your baby is getting enough: swallowing, diapers, and weight gain. Let’s walk through them.

What “enough” looks like overall
A baby who is getting enough breast milk typically:
- Nurses effectively (you see or hear swallowing and the feed has a rhythm)
- Has age-appropriate wet and dirty diapers
- Is gaining weight appropriately at follow-up visits
- Looks hydrated (moist mouth, good color, alertness between sleeps)
You do not need all the “nice-to-have” signs (like a sleepy milk-drunk finish) to feel confident. Diapers and weight are the heavy hitters.
One more big-picture piece that helps at 3 a.m.: in the early days, most newborns feed often, usually about 8 to 12 times in 24 hours. Cluster feeding (back-to-back feeds) can be normal and does not automatically mean low supply.
Sign #1: You can hear or see swallowing
In the first days, babies often do a lot of quick sucking to get milk flowing, then move into a slower pattern once milk is transferring. Here’s what you’re looking for:
- Rhythmic suck-swallow-breathe after the first minute or two
- Audible swallows (sometimes a soft “kah” sound), or visible swallowing at the throat
- Deep jaw movement with pauses, not just tiny nibbling
Two helpful nuances:
- Some babies swallow quietly. If you do not hear much, watch for throat movement and little pauses in the sucking pattern.
- Swallowing may be subtle early on, especially before milk “comes in.” This usually ramps up around days 2 to 3, but there is a normal range. If milk volume does not seem to increase by day 4 to 5, call your baby’s clinician or a lactation consultant.

Sign #2: Wet diapers by age
Wet diapers are one of the best at-home hydration checks. In the earliest days, diaper counts usually climb quickly, but there is some variation.
Rule-of-thumb wet diaper expectations
- Day 1: often at least 1 wet diaper
- Day 2: often at least 2 wet diapers
- Day 3: often at least 3 wet diapers
- Day 4: often at least 4 wet diapers
- Day 5 and beyond: commonly about 6 or more wet diapers in 24 hours (some clinicians use 6 to 8)
A quick reality check: disposable diapers can feel deceptively dry. If you’re unsure, place a tissue inside the diaper for a feed or two and see if it becomes wet.
Call your baby’s clinician the same day if wet diapers are below the age expectations, especially after day 4, or if urine looks very dark and concentrated.
Seek urgent care now if your baby has no urine for 8 hours (or more) and is also hard to wake, very sleepy, or showing other signs of dehydration.
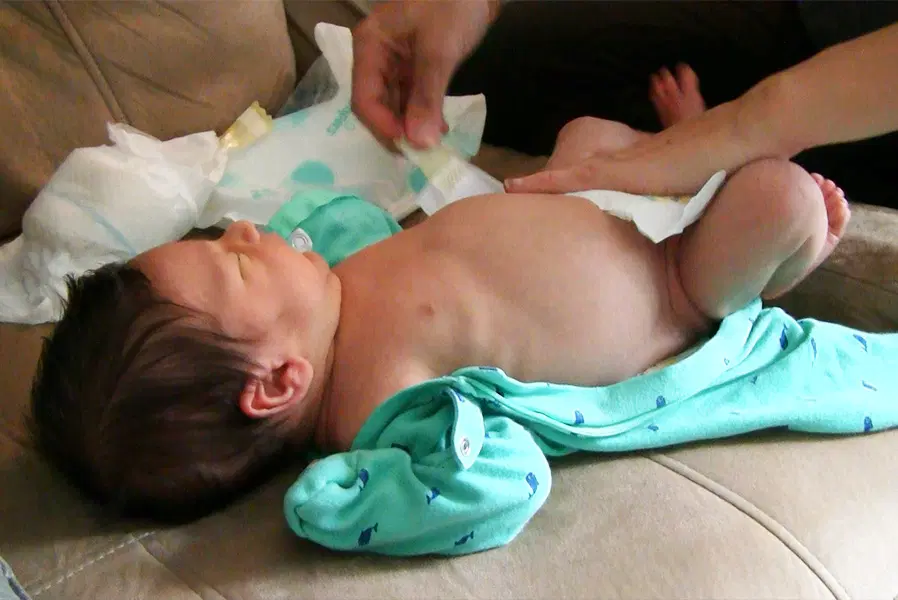
Sign #3: Dirty diapers by age
Poop is less glamorous but very informative, especially in the first week. Stools should transition as milk volume increases.
What stool changes you want to see
- Days 1 to 2: black, sticky meconium
- Days 3 to 4: greenish or brown “transitional” stools
- By days 4 to 5: yellow stools that are looser, often seedy or mustard-like
How often is “normal”?
Frequency varies, but as a general guide:
- First week: many babies stool multiple times per day as intake increases.
- After the first month: some breastfed babies stool after most feeds, and others go several days between poops. Both can be normal if baby is otherwise thriving.
A common early red flag: If stools are still meconium-like (black and sticky) or have not started transitioning by day 3 to 4, it is worth checking in with your pediatrician or a lactation consultant.
Sign #4: Weight checks matter most
I say this with love: sleep deprivation makes all of us unreliable narrators. Weight checks give us objective information.
What typically happens with weight
- It is normal for newborns to lose weight in the first days after birth.
- Most babies start gaining again once milk volume increases.
- Many babies return to birth weight by about 10 to 14 days.
Your pediatrician will interpret weight trends using your baby’s age, birth history, diaper output, and overall exam. If weight gain is slower than expected, your pediatrician may recommend a lactation evaluation, a feeding observation, or additional weight checks.
Important: Home scales can be helpful for some families, but they can also increase anxiety. If you find yourself weighing compulsively, it is okay to hand the scale over to someone else and let your clinic do the tracking.
Note for late-preterm babies (born 34 to 36 weeks), smaller babies, and babies with jaundice: they can tire out more easily and may not feed as effectively. The same signs still matter, but your thresholds and follow-up plan may need to be more individualized. When in doubt, get a watched feed and a weight check.
Other reassuring signs
These signs are supportive, but they are not as reliable as diapers and weight:
- Baby seems satisfied after many feeds (not all)
- Good muscle tone and periods of alertness between sleeps
- Moist mouth (lips and tongue not dry or sticky)
- Good color and warmth (pink and warm, not gray or mottled)
And yes, babies can be fussy for reasons that have nothing to do with milk volume. Newborns are new to earth. They have opinions.
When to get help
If you are on the fence, you are allowed to ask for help. You do not need to “earn” a lactation visit by reaching some crisis point.
Call the same day if:
- Wet diapers are below the rule-of-thumb expectations, especially after day 4
- Stools are not transitioning by day 4 (still black and sticky, or very scant)
- Baby is too sleepy to feed or repeatedly cannot stay awake long enough to nurse
- Feeds are consistently very long with little swallowing, or baby seems frustrated at most feeds
- You have significant nipple pain beyond initial tenderness, cracking, bleeding, or pain that makes you dread feeding
- You suspect latch or tongue mobility issues (clicking, slipping off, shallow latch, poor seal)
- Your milk has not increased by about day 4 to 5, or baby still seems to be working hard with minimal swallows
Seek urgent care now if your baby:
- Has signs of dehydration (very dry mouth, sunken soft spot, markedly decreased urination)
- Is hard to wake, very floppy, or unusually weak
- Has blue lips or breathing trouble
- Has a fever (in infants under 3 months, a rectal temperature of 100.4°F / 38°C or higher needs immediate medical evaluation, follow your local urgent care or emergency guidance)
- Looks more yellow or is not feeding well (worsening jaundice or jaundice plus sleepiness or poor intake needs same-day evaluation, bilirubin testing is what decides next steps)
If something feels off, trust that instinct and get eyes on your baby. A quick weight check and a watched feeding can bring massive clarity.
Latch basics (quick and practical)
A good latch tends to look and feel like:
- Wide mouth before latching
- Lips flanged (not tucked in)
- More areola visible above the top lip than below the bottom lip (often, not always)
- Strong tugging, not sharp pain after the initial latch-on moment
If you are wincing through feeds or your nipples are coming out creased or lipstick-shaped, that is a good reason to get a feeding observed.
Myths that make parents panic
“My baby wants to nurse again an hour later, so I must not have enough milk.”
Frequent feeding can be completely normal, especially in the early weeks. The question is whether baby is transferring milk (swallowing), making diapers, and gaining weight.
“My breasts feel softer, so my supply must have dropped.”
Breasts often feel less engorged once your body adjusts to your baby’s needs. Soft breasts can still make plenty of milk.
“I can’t pump much, so baby must not be getting much.”
Pumping output is not a perfect measure of what a baby can remove at the breast. Babies are often more efficient than pumps.
Quick checklist
- I notice swallowing during at least some feeds.
- Wet diapers match my baby’s age (especially 6 or more per day after day 5).
- Poop is transitioning in the first week (moving toward yellow by days 4 to 5).
- My baby is being followed with weight checks and the trend is acceptable.
If you can check most of these boxes, odds are very good your baby is getting enough. If you cannot, or if you are just scared, a pediatric or lactation check is a smart next step, not an overreaction.

FAQ
How long should a breastfeeding session be?
There is a wide normal range. Some babies are efficient and finish in 10 to 15 minutes, others take longer. Time matters less than milk transfer (swallowing), diaper output, and weight gain.
Can my baby be getting enough if they fall asleep at the breast?
Sometimes yes. Newborns are sleepy. What matters is whether feeds include active swallowing and whether diaper counts and weight gain are on track. If your baby is consistently too sleepy to feed effectively, that deserves a same-day check.
What if my baby has plenty of wet diapers but hardly any poop?
After the first month, this can be normal for some breastfed babies. In the first week, low stool output or stools that are not transitioning can signal low intake and should be discussed with your baby’s clinician.
What if I am supplementing sometimes?
You can still use the same adequacy signs: diapers, weight gain, and your baby’s overall hydration and alertness. If supplementing is happening because of intake concerns, it is worth getting a feeding observed by your pediatrician or a lactation consultant so you have a clear plan and good follow-up.
Sarah Mitchell
Sarah Mitchell is a Registered Pediatric Nurse and a mother of three who has spent over a decade helping families navigate the beautiful, chaotic early years of childhood. She combines evidence-based medical knowledge with real-world parenting experience to offer practical, compassionate advice. At Awesome Parent, Sarah's mission is to help exhausted parents find solutions, trust their instincts, and finally get some sleep.


