
A calm, evidence-based way to check if your baby is getting enough breast milk: swallowing, diaper counts, weight gain, and red flags that need a lactation o...
Nipple Shields While Breastfeeding: When They Help and How to Stop

Sarah Mitchell
Sarah Mitchell is a Registered Pediatric Nurse and a mother of three who has spent over a decade helping families navigate the beautiful, chaotic early years of childhood. She combines evidence-based medical knowledge with real-world parenting experience to offer practical, compassionate advice. At Awesome Parent, Sarah's mission is to help exhausted parents find solutions, trust their instincts, and finally get some sleep.
At 3 AM in our house, a nipple shield has absolutely been the difference between “I can do this” and “I’m done.” I used to see nipple shields in clinic as either a miracle or a menace, depending on who you asked. The truth, like most parenting truths, is calmer than that: a nipple shield is a tool. When it fits well and you have a plan, it can protect healing tissue and help a baby practice latching. When it is used long-term without checking milk transfer, it can sometimes chip away at supply.
Let’s walk through when nipple shields can help, how to tell if your baby is actually getting milk through it, and a gradual, realistic way to stop using one.

What a nipple shield is and what it is not
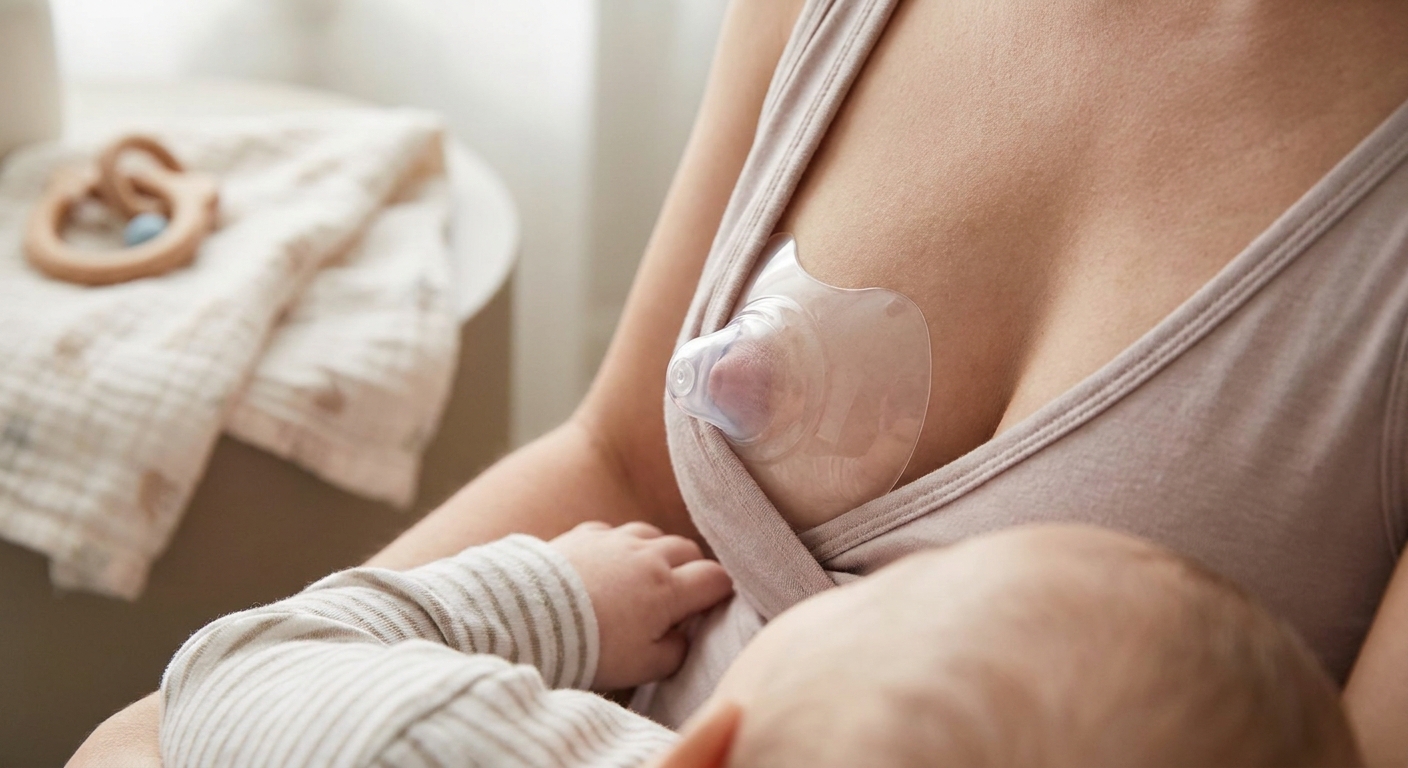
A nipple shield is a thin cover (usually silicone) that sits over the nipple during breastfeeding. Depending on the brand and size, it may also cover part of the areola. It gives the baby a firmer surface to latch onto and can reduce friction on sore or damaged nipples.
What it is not: a fix for every breastfeeding problem. Most latch and pain issues improve fastest when the underlying cause is addressed (positioning, attachment, flow, baby’s stamina, nipple trauma). A shield can buy you time and comfort while you get that support.
When nipple shields can help (temporarily)
In my nursing brain, I put “good nipple shield situations” into a few buckets. These are the scenarios where a shield is often used as a bridge, not a final destination.
- Baby is premature or very sleepy and has trouble maintaining a latch long enough to transfer milk.
- Baby struggles to latch in the early days (especially during engorgement) and keeps popping off.
- Flat or inverted nipples that make it difficult for baby to get a deep latch right now.
- Severe nipple pain from shallow latch or early damage while you work on positioning and healing.
- Transitioning from bottle to breast when baby prefers a firmer feel in the mouth.
If you’re thinking, “That’s me, but I’m still in agony,” keep reading. Pain is information, and shields should make feeding more comfortable, not more complicated.

When a nipple shield is not a good idea
Sometimes a shield is the wrong tool, or it is a tool that needs closer follow-up. Consider getting hands-on help from an IBCLC (International Board Certified Lactation Consultant) if any of the following are true:
- Baby is not gaining weight well or you are being asked to do frequent weight checks.
- You have low milk supply or a history of supply issues and the shield is being used for many feeds per day.
- Baby feeds for a long time (45 to 60 minutes) and still seems hungry soon after.
- You feel little to no breast softening after feeds, or you are getting recurrent clogged-feeling areas.
- Your nipples are getting worse (more cracking, bleeding, or new bruising) despite the shield.
A shield can be part of a safe plan, but I like to see a plan that includes two things: a way to confirm milk transfer and a way to transition off when baby is ready.
Using a nipple shield correctly
Most nipple shield frustration comes down to fit or placement. If the shield is too large, baby can slip and “chew.” If it is too small, it can pinch or restrict flow. Many parents also place the shield only on the nipple tip, which makes a shallow latch more likely.
Quick setup checklist
- Choose the right size: shields come in different diameters (often measured in millimeters). Sizing is based on your nipple diameter, not the size of your areola, and sizing varies by brand. If you are unsure, an IBCLC can size you quickly.
- Moisten the rim with a few drops of water or expressed milk so it adheres better.
- Flip the shield halfway inside out, place the tip centered over your nipple, then flip the rim back down. This helps draw nipple tissue into the tip.
- Bring baby to breast with a wide mouth, aiming the nipple (and shield) toward the roof of baby’s mouth for a deeper latch.
If the shield collapses, whistles, slides around, or you hear clicking through most of the feed, that is a sign to reassess latch and fit.
How to tell if milk is transferring
This is the part I care about most as a nurse: comfort is important, but milk transfer is what protects your baby’s growth and your milk supply.
Signs baby is getting milk
- You see and hear swallowing after an initial burst of quick sucks (look for a suck-suck-swallow rhythm).
- Baby’s jaw moves deeply with pauses, not just tiny fluttery sucks the entire time.
- Your breasts feel softer after feeds, especially in the first weeks.
- Diapers are on track: after day 4 to 5, many babies have around 6 or more wet diapers per day. Stool patterns are more variable and change with age, so diaper counts are just one piece of the picture and your clinician may give you baby-specific targets.
- Weight gain is appropriate at checkups.
Signs milk transfer might be low
- No audible swallowing even after your milk lets down (when milk starts flowing more strongly).
- Baby falls asleep quickly and wakes hungry very soon, feed after feed.
- Long feeds with little satisfaction, especially if baby seems frantic afterward.
- Very little milk visible in the shield during the feed. This is only a clue, because some babies transfer well without much milk pooling in the shield.
- Declining pump output (if you are pumping) or breasts never feel relieved.
If you’re unsure, one of the most reassuring options is a weighted feed with a lactation consultant. It is exactly what it sounds like: baby is weighed before and after a feed on a sensitive scale to estimate intake, and the results are best interpreted alongside diaper output, weight trends, and what the feeding looks like.
Protecting your supply with a shield
Some parents can use a shield and keep a strong supply with no extra steps. Others may need a little backup, especially in the first couple weeks when your supply is getting established.
- Feed frequently, following hunger cues, and avoid long stretches without milk removal in the early weeks when possible.
- Use breast compressions during feeds to keep milk flowing when baby’s sucking slows.
- Consider pumping after some feeds if baby is not transferring well, you are dealing with sleepy feeds, or you are instructed to by your care team.
- Track diapers and weight, especially while you are figuring out shield fit and technique.
If pumping becomes part of your routine, it does not have to be forever. Think of it as a temporary helper, like the shield itself.

Special cases to keep in mind
Sometimes a shield helps, but it can also hide the “why” underneath. A few examples I see often: a baby with a high palate who struggles to stay latched, tongue function issues that make it hard to maintain suction, or a very strong letdown where baby pops off sputtering. A shield may make feeds feel more manageable in the moment, but it is still worth getting a skilled set of eyes on the latch so you are not stuck using it longer than you want.
Pain and damage checks
Some tenderness in the very early days can happen, but sharp pain, worsening pain, or visible damage deserves a closer look. A nipple shield should reduce friction and help you heal, not create new trauma.
Get help soon if you notice
- Cracked nipples, bleeding, blisters, or open sores that are worsening or not starting to improve within 24 to 48 hours after you make latch and positioning changes.
- Severe pain that continues throughout the entire feed (not just the first few seconds).
- Nipple looks creased, flattened, or lipstick-shaped after feeding, which often points to a shallow latch.
- New or worsening bruising on the areola.
- Baby cannot stay latched even with the shield, or feeds are consistently ineffective.
Get urgent care the same day if you have
- Fever or flu-like symptoms along with breast pain, especially if symptoms are severe or rapidly worsening.
- A hot, red, rapidly spreading area on the breast.
- Severe breast pain with swelling and you feel very unwell.
One more gentle reminder: concerns like nipple thrush, milk blebs, and tongue tie have their own dedicated deep dives because they each require a specific approach. If your symptoms strongly suggest one of those, you will get clearer help by focusing on that specific issue with your clinician or lactation consultant.
How to stop using a nipple shield
Most babies do best with a slow transition. The goal is not “rip off the shield and hope for the best.” The goal is comfortable feeds with good transfer, one small win at a time.
Step 1: Pick your easiest feed
Choose the time of day when your baby latches best, often the first morning feed or when baby is calm but hungry.
Step 2: Start with a warm-up
Begin the feed with the shield so baby is already sucking and milk is flowing. After 1 to 3 minutes, when swallowing is happening and baby is less frantic, gently break the latch.
Step 3: Try without the shield
- Remove the shield.
- Re-latch baby skin-to-skin if possible.
- If baby latches, keep the feed going until it stops being effective or becomes uncomfortable.
If baby gets upset, pop the shield back on and finish the feed. That is not “failure.” That is practice.
Step 4: Repeat once a day, then build
Do one no-shield attempt per day for a few days, then increase to two. Many babies transition off the shield over 1 to 3 weeks, sometimes sooner.
Step 5: Nudge the latch in your favor
- Try different positions (laid-back nursing, football hold, side-lying). A new angle can change everything.
- Shape the breast with a gentle “sandwich hold” to help baby take a bigger mouthful.
- Hand express a little milk before latching so baby gets an instant reward.

Common transition hiccups
“My baby screams when I take it off.”
Totally common. Try removing it mid-feed after milk is flowing, or offer a brief calm reset: skin-to-skin, bounce, a few deep breaths, then re-latch. Some babies also do better when slightly drowsy.
“My nipple hurts immediately without it.”
That usually points back to latch depth. A shield can sometimes mask a shallow latch just enough that you can survive the feed, but it does not fix the mechanics. Getting eyes on a feed is the fastest way forward.
“My supply dropped after starting the shield.”
Do not panic, but do respond. If milk removal decreased, your body may have downshifted. Temporarily adding pumping after feeds (or a few times per day) while you work on latch and transition off can help protect supply.
Cleaning and replacing your shield
Follow the manufacturer’s instructions, but general safety tips are:
- Wash with hot, soapy water after each use and rinse well.
- Allow to air dry completely on a clean surface.
- Replace if damaged: tears, cloudiness that does not wash off, sticky texture, or misshapen edges.
If you are using a shield multiple times a day, having a backup can save your sanity when one is drying and a hungry baby is not interested in waiting.
FAQ
Can a nipple shield cause nipple confusion?
Some babies are more sensitive to different textures and flow, but many use a shield and transition off without any issues. The bigger concern is usually milk transfer and supply protection, not confusion. If baby is struggling at breast, get support early.
How long can I use a nipple shield?
Some families use one for a few days, others for weeks. I like a check-in if you are still using it regularly after the first week or two, especially if weight gain or supply is a concern. A plan plus follow-up makes longer use safer.
Should I feel pain with a nipple shield?
You might feel mild stretching or tenderness at first, but sharp pain, pinching, or worsening damage is a sign something needs adjusting (fit, latch, position, suction).
Do I need to pump if I’m using a shield?
Not always. If baby is gaining well and diapers are on track, you may not need to. If baby is sleepy at breast, feeds are long and ineffective, weight gain is slow, or your breasts never feel relieved, pumping can help protect supply while you troubleshoot.
A calm bottom line
If you are using a nipple shield right now, you are not taking a shortcut. You are using a legitimate tool. The two things that keep it safe are (1) making sure your baby is truly transferring milk and (2) having a gentle plan to transition off as soon as you can.
If you want the fastest path to comfortable, effective feeds, bring in a lactation consultant and let them watch a full feed. In the clinic, that one step solved more “mystery breastfeeding problems” than almost anything else, and it often gave parents immediate relief.
Sarah Mitchell
Sarah Mitchell is a Registered Pediatric Nurse and a mother of three who has spent over a decade helping families navigate the beautiful, chaotic early years of childhood. She combines evidence-based medical knowledge with real-world parenting experience to offer practical, compassionate advice. At Awesome Parent, Sarah's mission is to help exhausted parents find solutions, trust their instincts, and finally get some sleep.


