A parent-friendly guide to spotting strep throat, testing, antibiotics, comfort care, and when symptoms mean it is time for urgent help.
Strep Carrier State in Kids: A Positive Test Without Symptoms

Sarah Mitchell
Sarah Mitchell is a Registered Pediatric Nurse and a mother of three who has spent over a decade helping families navigate the beautiful, chaotic early years of childhood. She combines evidence-based medical knowledge with real-world parenting experience to offer practical, compassionate advice. At Awesome Parent, Sarah's mission is to help exhausted parents find solutions, trust their instincts, and finally get some sleep.
Nothing spikes a parent’s stress quite like seeing POSITIVE next to a strep test when your kid is bouncing off the walls, eating snacks, and insisting they feel “fine.” I have had this exact conversation in triage more times than I can count, and I’ve been on the parent side of it, too.
A positive strep test in a child with no symptoms is often interpreted very differently than classic strep throat or scarlet fever. The key concept is something called the strep carrier state.

What it means to be a strep carrier
Group A Streptococcus (often called “strep”) can live in the back of some children’s throats without causing illness. When that happens, we call them a carrier.
Carriers:
- Have strep bacteria present in the throat.
- Do not have an active infection and usually feel well.
- Can test positive on a rapid strep test or throat culture even when another virus is the real reason they were tested.
One important nuance: a positive rapid strep test is usually very specific for the bacteria being there, but it cannot tell whether a child has a true, active strep infection or is simply carrying strep in the background. That is why clinicians always combine the test result with the child’s symptoms and exam.
Why a positive test in a well child is read differently
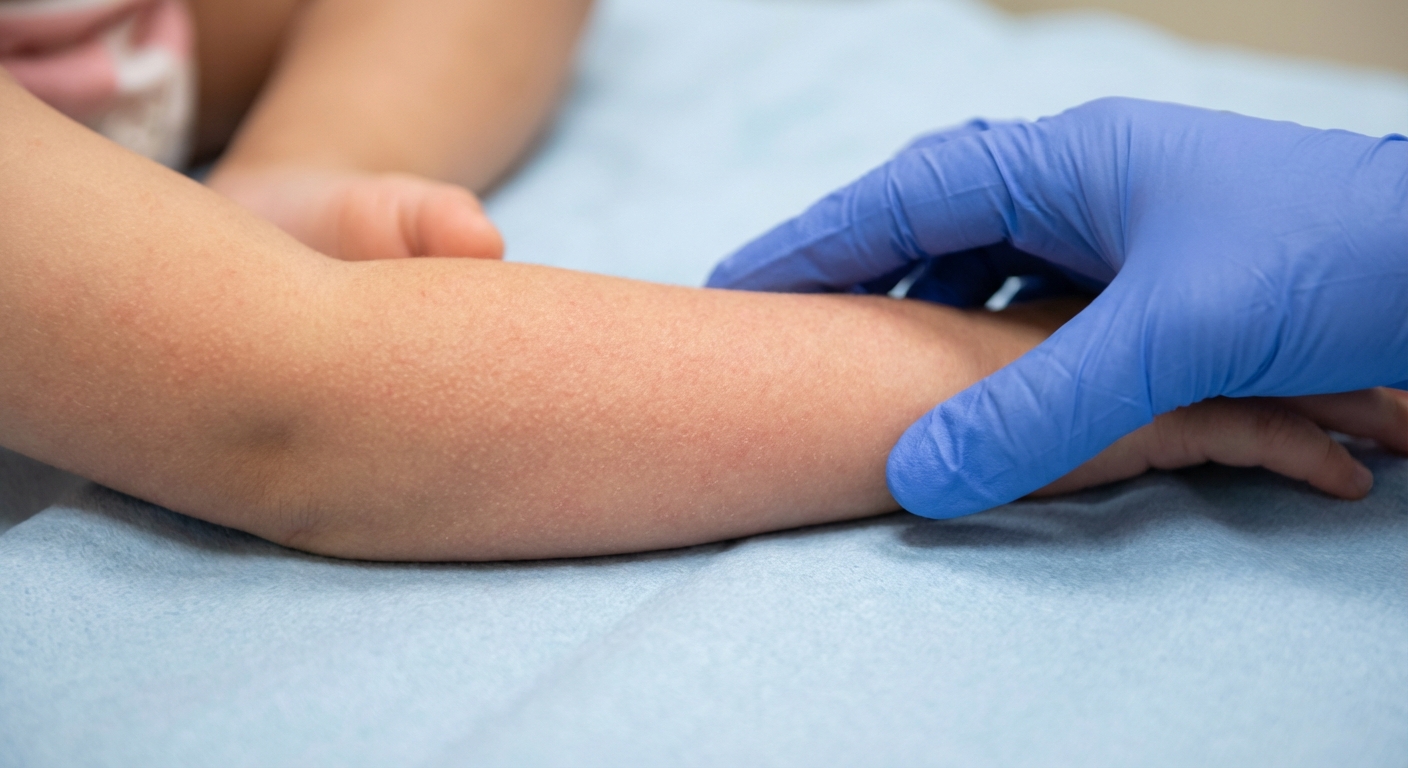
When a child is truly sick from acute strep throat (or scarlet fever, which is strep with a characteristic rash), the bacteria are the likely cause of the illness. Treating in that situation matters because antibiotics can modestly shorten symptoms (often by about a day, especially when started early) and, more importantly, help prevent rare but serious complications like acute rheumatic fever.
With a carrier, it’s different:
- The child’s immune system is not acting like there is an active strep infection.
- The positive test does not necessarily explain anything going on that day.
- Antibiotics are less likely to provide benefit and may cause side effects or contribute to antibiotic resistance.
Even more reassurance: the major immune complications we worry about (like acute rheumatic fever) are linked to untreated true strep throat. A child who is simply a carrier is generally considered low risk for those complications.
In triage terms: a positive test is a data point, not a diagnosis by itself. Clinicians interpret it in the context of the child in front of them.
How this happens
Common scenarios I see:
- They were tested because someone else in the house has strep and the family is worried.
- They have viral symptoms (like a runny nose or cough) and get tested “just to be safe.” A carrier can be positive even when the virus is the culprit.
- They recently had strep and still test positive afterward. That can happen if they were a carrier to begin with, if they became colonized again, or occasionally if bacteria linger even after appropriate treatment. This is one reason “test of cure” is usually not helpful in routine cases.
- A clinician includes a throat swab while evaluating fever or swollen lymph nodes, even if the throat is not the main complaint.
Carriage is more common in school-age kids than in toddlers, simply because older kids have more exposure in classrooms, sports, and playgroups.

Is a strep carrier contagious?
This is the question parents actually want answered at 2 a.m.
In general, strep carriers are much less likely to spread Group A strep compared with kids who have an active infection. The simplest parent-facing takeaway is: carriers are usually lower risk for transmission.
Also, remember that cough and runny nose are more typical of viral illness than classic strep throat. So if your child is coughing and sneezing, the germs most likely being sprayed around the house may be viral, even if the strep test happens to be positive.
That said, households are complicated. Kids share cups, forget what personal space is, and wipe their noses with their sleeves. So while carriage is generally considered lower risk for transmission, clinicians still look at the big picture, especially if there are repeated infections in a family.
When clinicians sometimes treat carriers anyway
Most strep carriers do not need antibiotics simply to “clear” the throat. But there are specific situations where clinicians may recommend treatment to eradicate carriage, even if the child feels well.
When treatment may be considered
- A household history of acute rheumatic fever (or unusually high concern for it). In these families, clinicians may be more proactive.
- Ongoing, repeated strep infections within the household or close contacts, especially if it looks like the same cycle keeps restarting.
- A community outbreak of acute rheumatic fever or invasive Group A strep where public health guidance advises a lower threshold for eradication.
- Before considering tonsil surgery primarily for recurrent strep, some specialists try to distinguish true recurrent infections from viral illnesses plus carriage.
- High-anxiety situations where positives keep driving repeated urgent visits. This is not a medical reason by itself, but in real life, some clinicians weigh family stress and follow-up burden when deciding next steps.
If eradication is attempted, clinicians may choose a regimen that can be more effective at clearing carriage than standard first-line therapy for strep throat. This is very individualized and depends on allergy history, local guidance, and your child’s medical background, so this is firmly a “follow your clinician’s plan” category, not a DIY one.
When clinicians evaluate household contacts
Parents are often surprised to learn that we do not routinely test or treat everyone in the family just because one child has strep, and that is even more true when the “positive” child is likely a carrier.
That said, there are times clinicians do consider treating or evaluating close contacts:
- Someone in the home is high risk, such as a person with a history of rheumatic fever, certain immune conditions, or other medical vulnerabilities where complications would be especially concerning.
- Multiple confirmed strep cases are happening back-to-back in a household, suggesting transmission within the home rather than random exposure.
- A close contact has clear symptoms consistent with strep and a positive test. That symptomatic person should be treated based on their own illness.
- Public health guidance during an outbreak recommends a broader approach.
In practice, a pediatrician may focus on the family pattern: Who is actually getting sick? How often? Are the positives tied to symptoms or popping up incidentally?

Why repeat tests often do not help
If your child is a carrier, a repeat rapid test or culture can stay positive for a long time, even when there is no active infection. That can lead to a frustrating loop:
- Test is positive.
- Child feels fine.
- Family retests to “make sure it’s gone.”
- Test is still positive.
- Everyone panics again.
Clinicians usually avoid a “test of cure” in routine situations because it rarely changes management and it can push families toward unnecessary antibiotics.
When a repeat test might make sense
There are exceptions. A clinician may consider repeat testing if:
- Your child has new, convincing symptoms later on and the question is whether this is a new infection.
- There is an unusual household risk factor, like a close contact with prior rheumatic fever.
- A specialist is working through recurrent strep questions and needs a clearer pattern over time.
But for a well child, repeating the test simply to chase a negative is usually not the best use of anyone’s energy.
When not to test for strep
This is a big one, because it helps prevent the whole “positive test, but they seem fine” spiral.
Many clinicians are less likely to test for strep when a child has features that strongly suggest a virus, such as:
- Cough
- Runny nose
- Hoarseness
- Oral ulcers
That does not mean a child can never have strep and a cough, but in general, those symptoms make strep less likely and make a carrier-state positive more likely to confuse the picture.
How clinicians tell carriage from true infection
There is no single at-home clue that proves carriage, but clinicians use a combination of:
- Symptoms and exam: Does the child look and act sick in a way that fits strep (sudden sore throat, fever, tender neck glands, no cough)?
- Pattern over time: Are there repeated positives with minimal symptoms, especially during viral seasons?
- Response to treatment history: Do symptoms consistently improve in a strep-timed way, or do positives seem unrelated to how the child feels?
In some cases, clinicians will document that a child is a likely carrier so future visits do not automatically trigger the same testing and antibiotic cycle.
What you can do at home
If your pediatrician thinks your child is a carrier and your child feels well, your job is mostly the unglamorous basics that actually help families the most:
- Keep up with handwashing for everyone, especially after blowing noses and before meals.
- Avoid sharing drinks and utensils as much as your household reality allows.
- Replace toothbrushes only if your clinician recommends it for your situation. For carriers, toothbrush swapping is not the magic fix people hope it is.
- Watch for true illness in the days ahead. If new symptoms show up, check in with your pediatrician rather than automatically re-testing at home.
And most importantly: you are not doing anything wrong. Carriage is common, and it is not a sign of poor hygiene or a “weak immune system.” It is a normal-by-kid-standards quirk of sharing germs in group settings.
School and daycare
For true strep throat that is being treated, many school and daycare policies allow return after a child has been on antibiotics for about 24 hours and is improving. For a child who is well and likely a carrier, return rules can vary by school, so it is reasonable to ask your pediatrician and check your local policy.
When to call your pediatrician promptly
Even when we are talking about carrier state, I want parents to trust their gut. Call your child’s clinician promptly if:
- Your child develops a new fever or looks increasingly unwell.
- There is significant trouble swallowing, drooling, or muffled voice.
- Your child shows signs of dehydration (very dry mouth, peeing much less, lethargy).
- A close contact has a history of rheumatic fever or your child has special medical risk factors.
- There are repeated strep diagnoses in the household and you feel stuck in a cycle.
Those situations are less about the test result itself and more about the overall risk and how your child is doing clinically.
Quick FAQ
Can my child have a virus and still test positive for strep?
Yes. This is one of the most common ways carrier state shows up. The virus causes the symptoms, and the strep test turns positive because strep is living in the throat in the background.
Does a positive rapid strep test always mean my child needs antibiotics?
No. A positive test means strep is present, but it does not prove it is causing the current symptoms. In a well child, clinicians consider carriage and weigh whether treatment provides benefit in your specific situation.
Will my child outgrow being a strep carrier?
Many kids do not stay carriers long-term. Carriage can come and go over months and years, especially with changing exposures at school or daycare.
Should we test siblings just in case?
Usually not if they are well. Testing well siblings often creates more confusion than clarity. If a sibling becomes symptomatic, that child should be evaluated on their own.
Why did my child get a throat culture after a negative rapid test?
In children, many clinics back up a negative rapid test with a throat culture when symptoms strongly suggest strep. It is a safety net to avoid missing a true infection.
Sarah Mitchell
Sarah Mitchell is a Registered Pediatric Nurse and a mother of three who has spent over a decade helping families navigate the beautiful, chaotic early years of childhood. She combines evidence-based medical knowledge with real-world parenting experience to offer practical, compassionate advice. At Awesome Parent, Sarah's mission is to help exhausted parents find solutions, trust their instincts, and finally get some sleep.