A calm, parent-friendly guide to newborn jaundice: what causes it, how to check for yellowing, what’s normal vs concerning, and when to seek urgent care.
Jaundice in a Formula-Fed Newborn

Sarah Mitchell
Sarah Mitchell is a Registered Pediatric Nurse and a mother of three who has spent over a decade helping families navigate the beautiful, chaotic early years of childhood. She combines evidence-based medical knowledge with real-world parenting experience to offer practical, compassionate advice. At Awesome Parent, Sarah's mission is to help exhausted parents find solutions, trust their instincts, and finally get some sleep.
One of the most common questions I got as a pediatric triage nurse sounded like this: “My baby is formula-fed. So why do they look yellow?” Usually that call came late at night, with a worried parent holding their newborn under every light in the house.
Here’s the calm truth: formula-fed babies can absolutely get jaundice. Feeding method matters in some patterns of jaundice, but it does not “immunize” a newborn against turning yellow.

Below I’ll walk you through why jaundice happens, what’s typical for formula-fed newborns, how it differs from jaundice linked to breastfeeding, and the specific symptoms that deserve a same-day call to your baby’s clinician.
Quick refresher: what jaundice is
Jaundice is the yellow tint you may notice in your baby’s skin or the whites of their eyes. It happens when a substance called bilirubin builds up faster than a newborn’s body can clear it.
Bilirubin comes from the normal breakdown of red blood cells. The body processes it in the liver, then excretes it in bile into the gut so it leaves the body mostly in stool.
Newborns, especially in the first days of life, are still ramping up that system. So jaundice is common, and in many babies it is temporary and mild. The key is knowing when it is expected and when it is a sign your baby needs to be seen.
Why a formula-fed baby can still look yellow
In formula-fed newborns, the most common reason for yellow coloring is the same reason it happens in many breastfed newborns: normal newborn physiology.
Common reasons include
- Normal “newborn jaundice”: Many babies have a bilirubin rise after birth because they are breaking down extra red blood cells and their liver is still learning the job. In many term babies, jaundice shows up after the first 24 hours and tends to peak around days 3 to 5.
- Not enough intake in the first days: Even with formula, some babies are sleepy, have a weak suck or seal on the bottle nipple, take small volumes, or spit up frequently. Less milk in can mean less stool out, and bilirubin leaves the body through stool.
- Bruising from delivery: A difficult or fast birth can cause bruising or a scalp hematoma. As that blood breaks down, bilirubin can rise.
- Blood type incompatibility: Some babies have jaundice because their red blood cells break down faster due to ABO incompatibility or Rh disease between the birthing parent and baby. (Rh disease is less common now because of pregnancy prophylaxis, but it still matters.) This has nothing to do with formula versus breastmilk.
- Prematurity or early-term birth: Babies born early often clear bilirubin more slowly.
If your baby is formula-fed and looks yellow, it does not automatically mean anything is “wrong” with the formula or with how you’re feeding. It means your baby needs the same thing any jaundiced newborn needs: good intake, close observation, and the right follow-up.
Breastfeeding-related jaundice
Parents often hear “breastfeeding jaundice” and assume formula-fed babies cannot get jaundice. What’s really going on is that there are a couple of jaundice patterns that are more strongly associated with breastfeeding.
1) Breastfeeding jaundice (early)
This is less about breastmilk itself and more about low intake in the first days while milk supply is establishing. If a baby is not getting enough volume, they may not stool as much, and bilirubin can build up.
Formula-fed babies can have an intake issue too, but it tends to be less common because volumes are easier to measure. Still, sleepiness, nipple flow issues, mixing errors, or feeding schedules that stretch too long can lead to a baby getting less than they need.
2) Breast milk jaundice (later)
This is the one many people mean when they say “breastfeeding jaundice.” In some healthy, thriving breastfed babies, jaundice can linger longer. The baby usually feeds well, gains weight, and seems otherwise fine.
Formula-fed babies can still have prolonged jaundice, but when a formula-fed baby stays yellow beyond the early newborn period, clinicians think more broadly about other causes. That does not mean something scary is happening, but it does mean it should be evaluated rather than assumed to be “normal.”
What jaundice looks like
Jaundice often starts on the face and moves downward toward the chest, belly, arms, and legs. It can be more noticeable in natural daylight near a window than under warm indoor bulbs.
One important note: visual checks are less reliable in babies with deeper skin tones. That is another reason we do not rely on “eyeballing it” alone.
If there is any concern, your baby’s clinician can check bilirubin with a skin sensor or a blood test and decide whether your baby just needs monitoring, feeding support, or treatment.

Same-day call signs
If your newborn looks yellow, I want you to focus on more than color alone. The most important clues are how your baby is acting and what is coming out in diapers.
Call your baby’s clinician the same day if you notice any of the following.
Jaundice in the first day
- Yellowing that starts in the first 24 hours of life should be discussed promptly. Early jaundice can signal causes that need closer follow-up.
Sleepiness that interferes with feeding
- Your baby is hard to wake for feeds or falls asleep immediately at the bottle.
- You cannot get your baby to stay awake long enough to take an appropriate feed.
- Your baby seems floppy or unusually low-energy compared with earlier in the day.
Poor feeding
- Refusing the bottle repeatedly, or taking very little at most feeds.
- Weak suck, frequent slipping off the nipple, or feeding that takes an extremely long time because baby is too sleepy to coordinate.
- Repeated vomiting (not just small spit-ups) or signs of dehydration.
Concerning stool color
- Pale, chalky, or grayish stools (instead of yellow, mustard, or green-brown). This is not typical. It can be a sign bile is not reaching the intestines the way it should, and it needs prompt medical advice.
- No stooling for an unusually long stretch, especially paired with poor feeding.
Concerning urine color
- Very dark urine that looks tea-colored or brownish.
- Too few wet diapers for your baby’s age, or diapers that stay consistently dry. In general, wet diapers should increase day by day in the first week of life.
Also call the same day if the yellow color seems to be spreading quickly, becoming more intense, or if the whites of the eyes look increasingly yellow.
Go now: when it is an emergency
Most jaundice calls can be handled urgently but calmly, with a same-day visit or lab check. A smaller number need immediate evaluation.
Seek emergency care now if your newborn has jaundice and:
- Is difficult to wake and not feeding at all
- Has trouble breathing, persistent grunting, or looks blue or gray around the lips
- Has a fever. For many newborns and young infants, a rectal temperature of 100.4°F (38°C) or higher is treated as urgent. Follow your discharge instructions and local guidance.
- Has unusual high-pitched crying, extreme irritability, arching, or seems “off” in a way that worries you
If your gut is telling you something is wrong, trust it. I have never regretted a parent choosing to be cautious with a newborn.
What you can do at home
Home steps do not replace medical advice, but they can support your baby while you are arranging follow-up.
Focus on effective feeds
- Feed on a consistent schedule in the newborn period, even if that means waking a sleepy baby.
- If your baby is conking out at the bottle, try a diaper change halfway through, gentle un-swaddling, or skin-to-skin to keep them alert.
- Make sure the bottle nipple flow is appropriate. If it is too slow, baby may burn out. If it is too fast, baby may gulp, cough, and stop early.
Double-check formula prep
- Mix formula exactly as directed. Too concentrated can contribute to dehydration. Too diluted can reduce calories and intake.
Do not rely on sunlight as treatment
You might read that you should place your baby in a sunny window. I know why people suggest it, but it is not a safe or reliable treatment plan. Babies can overheat, get chilled, or be put in unsafe sleep positions. If you are worried about jaundice, the safest move is to talk with your clinician rather than trying to treat it with sunlight at home.
What your clinician may check
When you call about jaundice, your baby’s clinician is usually thinking about three big questions:
- How old is the baby? Timing matters because different causes cluster at different ages.
- How is feeding and hydration? Intake, weight checks, wet diapers, and stooling help show whether bilirubin is likely to rise further.
- Are there risk factors? Prematurity, bruising, family history of significant jaundice, or ABO or Rh incompatibility may change follow-up plans.
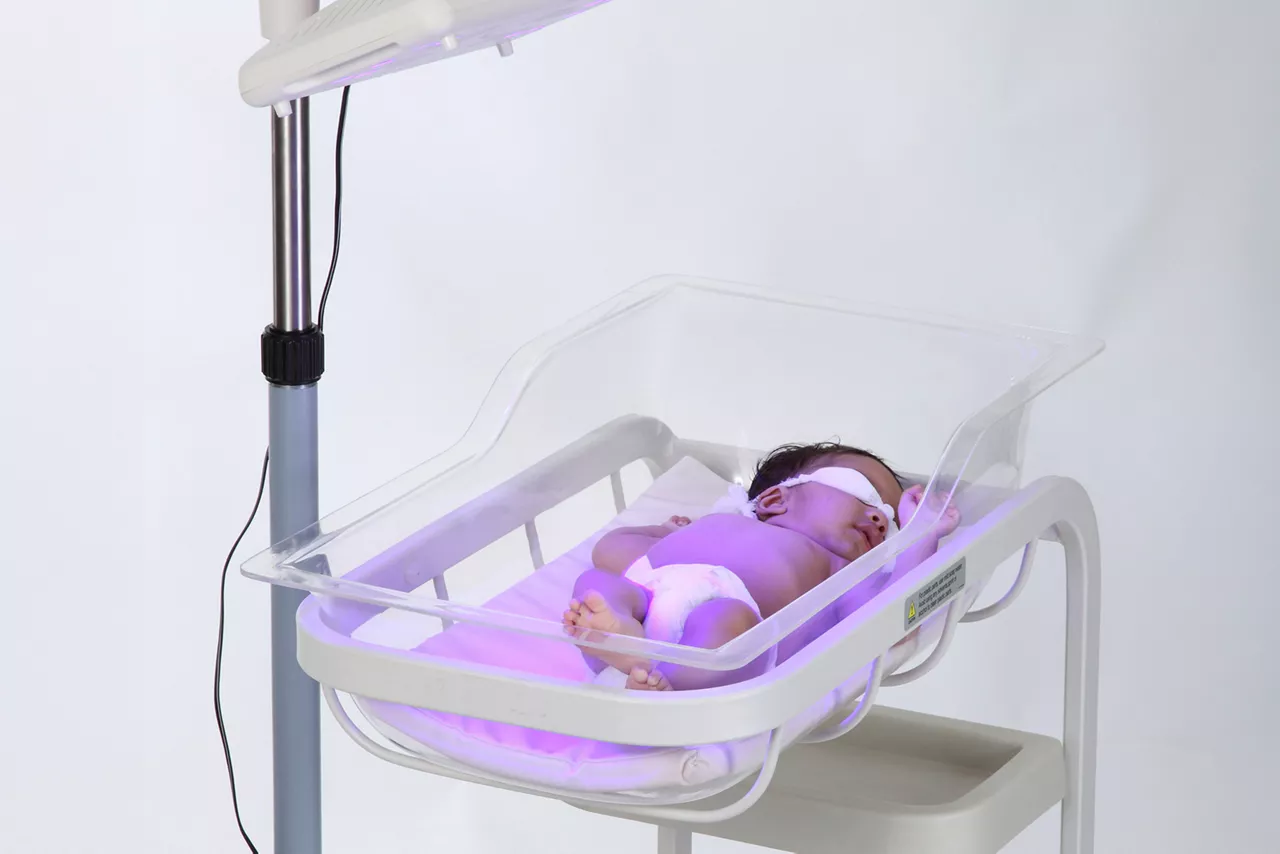
They may do a skin bilirubin screen, a blood test, weight check, and sometimes additional labs depending on the history and exam. If bilirubin is higher than desired for your baby’s situation, the treatment is typically phototherapy (special lights used under supervision). Your clinician will guide you without you needing to memorize any numbers.
FAQ
My baby is formula-fed and still yellow. Did I pick the wrong formula?
Almost never. Newborn jaundice is usually about normal newborn transitions, feeding effectiveness, or factors from birth, not the specific brand or type of formula. If your baby has vomiting, blood in the stool, rash, or severe fussiness, that is a separate conversation to have with your clinician.
Is jaundice worse at night?
Jaundice itself is not a “nighttime condition,” but it can look more noticeable at night because indoor lighting can exaggerate yellow tones. Check in natural daylight when you can, and focus on behavior and diapers, not color alone.
Can a formula-fed baby have jaundice that lasts more than a week?
Yes, it can happen. That said, if your baby is still noticeably yellow close to the two-week mark (or sooner if the yellowing is worsening), bring it up with your clinician so they can decide whether any additional evaluation is needed.
My baby is sleepy and jaundiced. Should I just let them sleep?
In the early newborn period, sleepiness that interferes with feeding is a reason to call the same day. Sleep is important, but so is getting enough milk in to help the body clear bilirubin.
The bottom line
A formula-fed newborn can look yellow for many of the same reasons any newborn does. The difference is not that formula prevents jaundice. The difference is that some breastfeeding-related jaundice patterns involve intake changes or longer-lasting yellowing that is more common in breastfed babies.
If your baby is yellow and also very sleepy, feeding poorly, peeing less, or has pale stools or very dark urine, make a same-day call. You are not overreacting. You are doing exactly what a newborn needs: getting help early.

Sarah Mitchell
Sarah Mitchell is a Registered Pediatric Nurse and a mother of three who has spent over a decade helping families navigate the beautiful, chaotic early years of childhood. She combines evidence-based medical knowledge with real-world parenting experience to offer practical, compassionate advice. At Awesome Parent, Sarah's mission is to help exhausted parents find solutions, trust their instincts, and finally get some sleep.