A calm, parent-friendly guide to newborn jaundice: what causes it, how to check for yellowing, what’s normal vs concerning, and when to seek urgent care.
Rh Incompatibility and Newborn Jaundice

Sarah Mitchell
Sarah Mitchell is a Registered Pediatric Nurse and a mother of three who has spent over a decade helping families navigate the beautiful, chaotic early years of childhood. She combines evidence-based medical knowledge with real-world parenting experience to offer practical, compassionate advice. At Awesome Parent, Sarah's mission is to help exhausted parents find solutions, trust their instincts, and finally get some sleep.
I still remember the first time a brand-new parent asked me, bleary-eyed in triage, “They keep saying I’m Rh-negative and the baby might get jaundice. What does my blood type have to do with my newborn turning yellow?” It is a totally reasonable question, especially when you are running on postpartum adrenaline and two hours of sleep.
Most newborn jaundice is normal and temporary. But jaundice tied to Rh incompatibility is different because it can be caused by red blood cells breaking down faster than usual. That can make bilirubin rise more quickly, which is why clinicians may watch your baby more closely.

Rh incompatibility, in plain English
“Rh” refers to an antigen (a marker), most commonly the D antigen, that can be present on red blood cells. If you have it, you are Rh-positive. If you do not, you are Rh-negative.
Rh incompatibility is the situation where a birthing parent is Rh-negative and the baby is Rh-positive. Here is the key distinction: a mismatch is common and usually not the problem by itself. The clinically important situation is when the parent becomes sensitized (also called alloimmunized) and makes antibodies that can attack Rh-positive red blood cells.
Why clinicians talk about anti-D antibodies
The specific antibodies we worry about are often called anti-D antibodies. “D” refers to the main Rh marker that causes most issues.
If an Rh-negative parent is exposed to Rh-positive blood (often during a prior pregnancy, miscarriage, abortion, ectopic pregnancy, or a bleeding event in pregnancy), their immune system may remember it and make anti-D antibodies later. In a future pregnancy with an Rh-positive baby, those antibodies can cross the placenta and attack the baby’s red blood cells.
That red blood cell breakdown is called hemolysis. Hemolysis creates more bilirubin than a newborn’s liver can comfortably process, so jaundice can appear earlier and climb faster.
How Rh-related jaundice is different
Many babies get “physiologic jaundice,” meaning a mild yellow color in the first days of life because newborn livers are still getting up to speed.
With Rh sensitization, the jaundice risk is tied to hemolytic disease of the newborn, where bilirubin can rise more quickly due to red blood cell breakdown.
Clues your care team is watching for
- Jaundice in the first 24 hours, which is a red flag clinicians evaluate for hemolysis or other causes
- A faster bilirubin rise compared with typical patterns
- Anemia (low red blood cell count) or signs the body is working hard to replace red blood cells
- More frequent bilirubin checks before discharge and after going home
Important note from a nurse who has seen too many parents blame themselves: none of this is caused by something you did during pregnancy. This is about immune system memory and blood type genetics.
RhoGAM and why it matters
RhoGAM is a brand name for Rh immune globulin. You may also hear it called “RhIG” or “anti-D immune globulin.” It is given to Rh-negative patients during pregnancy and after delivery (and after certain pregnancy events) to help prevent sensitization.
The basic idea
RhoGAM works by helping “mop up” any Rh-positive fetal blood cells that may have entered the parent’s bloodstream before the parent’s immune system has a chance to treat them like a threat and start building long-term anti-D antibodies.
When it is commonly given
Protocols vary, but in many places Rh immune globulin is given around 28 weeks of pregnancy, and again within 72 hours after delivery if the baby is Rh-positive. It is also often recommended after events that can mix blood, like bleeding in pregnancy, certain procedures, miscarriage, abortion, or ectopic pregnancy.
A quick bit of history
Before Rh immune globulin was widely used, Rh hemolytic disease was a much more common cause of severe newborn jaundice and serious newborn illness. RhoGAM has dramatically reduced those cases by preventing many parents from becoming sensitized in the first place.
If you received RhoGAM as recommended, that is reassuring. Your team may still monitor closely if there are reasons to suspect sensitization or if testing shows antibodies.
Testing you might hear about
Hospitals have slightly different routines, but if Rh incompatibility is on the radar, you may hear about:
- Parent blood type and antibody screen during pregnancy: checks Rh status and whether anti-D antibodies are present
- Baby’s blood type from cord blood or a newborn sample: confirms Rh status
- Direct antiglobulin test (often called DAT or Coombs test): looks for antibodies attached to the baby’s red blood cells
- Bilirubin checks: a skin reading and/or a blood test, depending on the situation
- Hemoglobin and hematocrit (in some cases): checks for anemia
What a positive DAT means (and what it does not)
A positive DAT supports the idea that antibodies are sticking to the baby’s red blood cells, which can happen in Rh disease and other immune mismatches.
But it is not a perfect crystal ball. Some babies with a positive DAT have only mild jaundice, and some babies can still develop significant jaundice even with a negative DAT. That is why your care team pays attention to the whole story: your antibody screen, baby’s exam, bilirubin trend, and anemia checks when needed.
If your baby needs repeat bilirubin checks, that does not automatically mean something is “going wrong.” It often means your care team is being appropriately cautious because bilirubin can rise faster in hemolytic jaundice.

Feeding support still matters
When bilirubin is rising, one of the most helpful, parent-powered tools is effective feeding. Feeding supports hydration and stooling, which helps the body move bilirubin out.
Feeding cannot “fix” the underlying antibody issue if hemolysis is happening, but it can make a meaningful difference in how well your baby clears bilirubin and how your baby feels.
If you are breastfeeding
- Aim for frequent feeds in the early days. Newborns often need to feed 8 to 12 times in 24 hours.
- Ask for a latch check. A tiny adjustment can turn a frustrating feed into an effective one.
- Watch output, not the clock. Your care team will ask about wet diapers and stools for a reason.
- Get help early if feeds are painful, baby is too sleepy to latch, or diapers are not increasing as expected. A lactation consultant can be invaluable here.
If you are formula feeding or combo feeding
- Feed on newborn cues and keep an eye on steady intake and wet diapers.
- Do not dilute formula to “flush bilirubin.” This is unsafe. If you are worried about intake, call your clinician.
- Ask about paced bottle feeding if baby is guzzling and spitting up a lot. Comfort matters too.
If a clinician recommends supplementation for a short period, it is not a failure. It is a tool to keep your baby well-fed while bilirubin is being closely monitored.
Hospital treatment
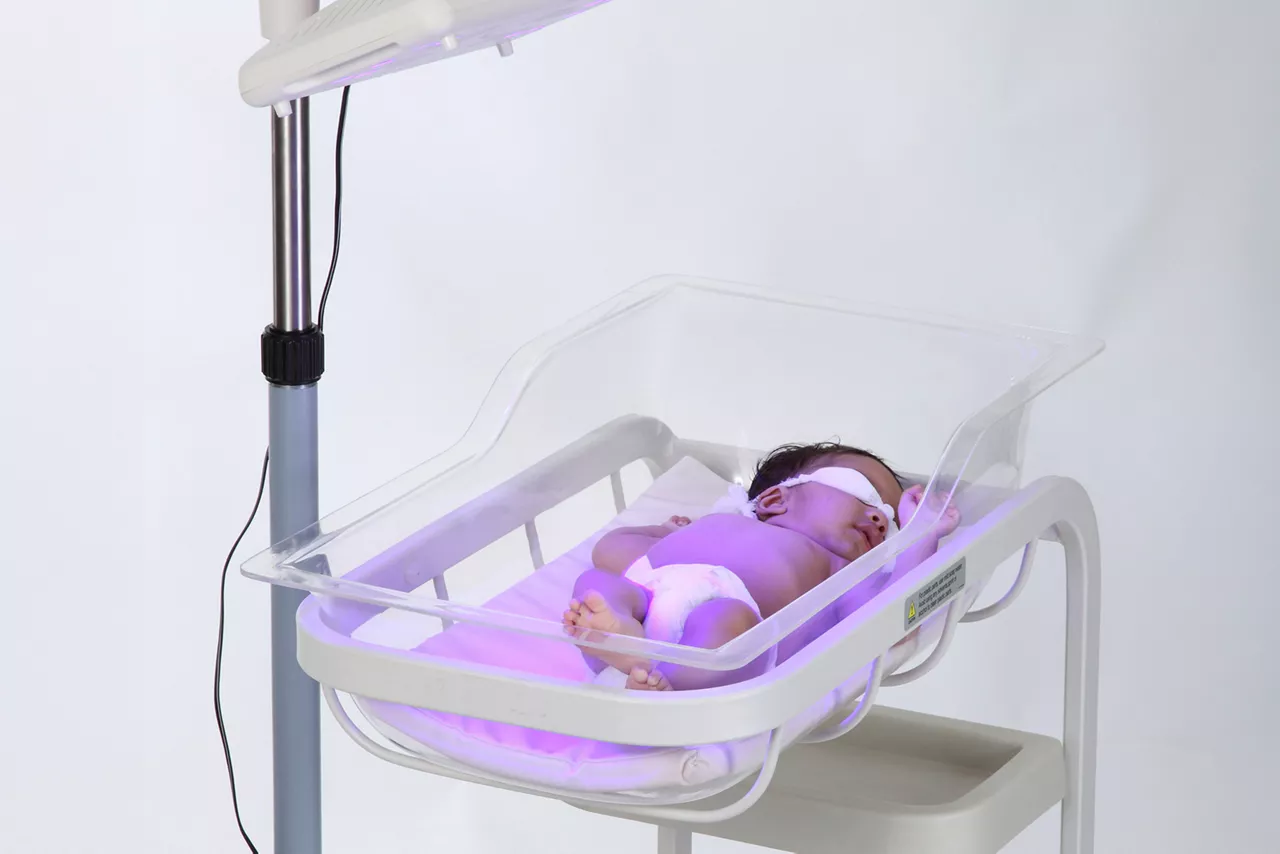
If bilirubin gets high enough or is rising quickly enough, your baby’s team may recommend treatment in the hospital. The most common treatment is phototherapy, where special lights help change bilirubin into a form the body can get rid of more easily.
In Rh hemolytic disease, teams may be quicker to recommend treatment because the bilirubin can climb faster. After stopping the lights, bilirubin can sometimes rebound, especially when hemolysis is involved, which is why some babies need a repeat level based on risk.
Whether your baby needs phototherapy or other hospital treatment is a clinician decision based on your baby’s age in hours, bilirubin trend, gestational age, overall exam, and risk factors. This is one of those situations where threshold charts floating around online can cause more panic than clarity, especially because the “right number” depends on several variables.
What you can expect with phototherapy
- Your baby may wear protective eye shields.
- Feeding continues. In fact, teams often encourage frequent feeding during phototherapy.
- Bilirubin levels are rechecked on a schedule to make sure they are responding.
- Your nurse can help you with ways to hold, soothe, and feed your baby while maximizing time under the lights.
Beyond phototherapy (less common)
If hemolysis is significant, the medical team may talk with you about additional options. These sound intense, but it helps to know what the words mean:
- IVIG (intravenous immune globulin): sometimes used in isoimmune hemolysis to reduce red blood cell breakdown in select situations.
- Exchange transfusion: rare today, but used when bilirubin is dangerously high or rising despite other treatment.
- Blood transfusion: sometimes needed later if anemia becomes significant.
If your team brings any of this up, ask them to walk you through the goal of each step and what they are watching for next.
Why OB teams screen so closely
When a pregnant patient is truly sensitized (alloimmunized), the concern is not only newborn jaundice after delivery. In more severe cases, the fetus can develop anemia during pregnancy, which is why obstetric teams follow antibody screens closely and may order extra monitoring when needed. Most families never get anywhere near that level, but it explains why your clinicians take these lab results seriously.
When to call urgently
Some jaundice can be watched with planned follow-up. But Rh-related jaundice is one reason clinicians take “yellow plus sleepy” seriously, especially early on.
Call your pediatrician right away or seek urgent care if your newborn:
- Looks more yellow quickly, especially spreading to the belly, arms, or legs
- Is hard to wake for feeds or cannot stay awake long enough to feed
- Is feeding poorly or has fewer wet diapers than expected for age
- Has a high-pitched cry, seems unusually floppy, or is difficult to console
- Has fever or seems unwell in any way that worries you
If you have been told there is Rh incompatibility, a positive DAT, or maternal antibodies, trust your gut and err on the side of calling. You will never be “too much” for asking about a newborn.
Common questions
Does an Rh-negative parent always have a jaundiced baby?
No. Many Rh-negative parents have babies who never develop problematic jaundice, especially when sensitization has been prevented with Rh immune globulin. The risk rises when anti-D antibodies are present or when testing suggests hemolysis.
I got RhoGAM. Can my baby still have jaundice?
Yes, because jaundice is common for many reasons. RhoGAM helps prevent Rh hemolytic disease, but it does not prevent normal newborn jaundice or other causes. If your baby has jaundice and you had RhoGAM, your care team will look at the full picture including timing, bilirubin trend, and blood tests.
Is Rh incompatibility the same as ABO incompatibility?
No. They are different types of blood group mismatch. ABO incompatibility involves the A, B, and O blood types and is managed a bit differently. If your clinician specifically mentioned Rh, it is worth keeping the conversation focused there so you get the right follow-up plan.
Can I do sunlight at home instead of phototherapy?
Please do not try to “treat” significant jaundice with sunlight. It is hard to do safely and effectively, and newborns can overheat or get chilled quickly. If phototherapy is needed, it is because your baby’s clinician believes monitored medical treatment is the safest option.
The bottom line
Rh incompatibility can lead to newborn jaundice when anti-D antibodies cause red blood cells to break down faster, pushing bilirubin up quickly. The reason your clinicians keep mentioning blood type, antibody screens, and close bilirubin follow-up is not to scare you. It is to catch a faster rise early, when it is easiest to treat.
Your job is not to memorize lab terms. Your job is to feed your baby as effectively as possible, keep follow-up appointments, and call if your baby is getting sleepier, yellower, or harder to feed. Their job is to decide if phototherapy or other hospital treatment is needed and to guide you step by step through it.
Sarah Mitchell
Sarah Mitchell is a Registered Pediatric Nurse and a mother of three who has spent over a decade helping families navigate the beautiful, chaotic early years of childhood. She combines evidence-based medical knowledge with real-world parenting experience to offer practical, compassionate advice. At Awesome Parent, Sarah's mission is to help exhausted parents find solutions, trust their instincts, and finally get some sleep.